
Introduction
Lung cancer is the most incident tumor in the world, with approximately 2.480.675 new cases annually and it is also the leading cause of cancer mortality, accounting for 1.817.469 deaths per year according to GLOBOCAN data.1 Data from the Spanish Group of Lung Cancer (GECP) Lung Cancer Observatory indicate that small-cell lung cancer (SCLC) constitutes 14.2% of registered cases, with an estimated 4,400 new diagnoses each year.2 SCLC is characterized by rapid proliferation, resulting in approximately 70% of new cases being diagnosed at advanced stages (extensive-stage SCLC [ESCLC]).3 The remaining 30% are diagnosed at limited stage (clinical stages I-III) and are treated with curative-intent chemotherapy plus radiotherapy followed by maintenance immunotherapy according to the ADRIATIC regimen.4 Before the introduction of durvalumab, 5-year survival for limited-stage SCLC with chemoradiotherapy ranged from 16.1% to 27.7%.5,6 With the addition of 2 years of durvalumab consolidation, median overall survival has improved to 33.4-55.9 months, with 3-year overall survival reaching 56.5%.4
In contrast, gastrointestinal stromal tumors (GIST) are rare mesenchymal neoplasms. Most GISTs harbor activating mutations in the KIT gene and show positive immunostaining for the KIT protein (CD117). The incidence in Spain is 1.1 cases/100,000 inhabitants/year, although it may be higher, as up to 30% of the population may harbor microscopic GIST foci. The median age at diagnosis is approximately 60 years. Before the introduction of adjuvant tyrosine kinase inhibitor therapy, 5-year overall survival for localized GIST treated with surgery was 70%. Before tyrosine kinase inhibitors became available, median overall survival in patients with metastatic disease was approximately 20 months. Imatinib, a KIT tyrosine kinase inhibitor, has dramatically altered the natural history of the disease; median overall survival for metastatic patients now exceeds 5 years.7
Synchronous tumors (or synchronous multiple primary malignancies) are defined as two or more primary malignant tumors diagnosed simultaneously or within the first 6 months following diagnosis of the first tumor (definition used by the International Agency for Research on Cancer). Some registries, such as the SEER program (Surveillance, Epidemiology, and End Results), apply a stricter 2-month interval.8 In this report, we present the case of a patient with synchronous diagnosis of limited-stage SCLC and metastatic gastric GIST with hepatic involvement, in whom both malignancies were treated simultaneously, resulting in remarkable clinical outcomes.
Case report
A 63-year-old male with type 2 diabetes mellitus and dyslipidemia, a heavy smoker (47 pack-years), and occasional alcohol consumption, who was independent in activities of daily living, presented in January-February 2025 with constitutional symptoms (8 kg weight loss) and progressive fatigue. An initial abdominal ultrasound revealed multiple hepatic lesions, prompting further diagnostic evaluation. On physical examination, he had an Eastern Cooperative Oncology Group (ECOG) performance status of 0, good general condition, and mild conjunctival icterus. Abdominal examination was notable for a hard hepatomegaly extending 4 cm below the costal margin, without signs of peritoneal irritation.
Contrast-enhanced thoraco-abdomino-pelvic computed tomography (April 2, 2025) showed a 5-cm spiculated mass in the anterior segment of the left upper lobe, associated with pathological left hilar lymphadenopathy (22 and 33 mm) and a precarinal node (22 mm), with significant (but incomplete) obliteration of the left pulmonary artery branch. There was massive hepatomegaly with multiple confluent solid focal lesions showing central hypodense areas (necrosis), consistent with extensive hepatic metastases. The exophytic lesions invaded the gastrohepatic ligament and lesser sac, with loss of fat planes with the stomach (lesser curvature and antrum), duodenum (first and second portions), and pancreas (displaced, infiltration not excluded). There was broad contact with the inferior vena cava and splenoportal axis, encasing the hepatic artery and its branches. The conclusion was polymetastatic liver disease plus a pulmonary mass with lymphadenopathy, suggestive of GIST with hepatic and thoracic metastases (second primary lung neoplasm not excluded).
Upper gastrointestinal endoscopy (April 2, 2025) revealed a 5-6 cm submucosal lesion in the greater curvature of the stomach with central ulceration, partially occluding the gastric lumen. Endobronchial ultrasound-guided transbronchial needle aspiration of stations 4L/4R (April 14, 2025) demonstrated metastasis of neuroendocrine SCLC. Immunophenotype was CK8/18 positive (paranuclear dots), INSM1 positive, synaptophysin positive, chromogranin A negative, and TTF-1 negative; Ki-67 90%. Gastric biopsies confirmed GIST, CD117 positive, and DOG1 positive, Ki-67 ≈10%. Percutaneous liver biopsy (April 29, 2025) confirmed metastatic infiltration by GIST (DOG1 positive). The final diagnosis was two synchronous tumors: limited-stage SCLC (T2b N2 M0) and metastatic GIST (gastric primary with extensive hepatic metastases) (Fig. 1). Staging was completed with brain CT and bone scintigraphy (April 29, 2025), both negative for metastases.
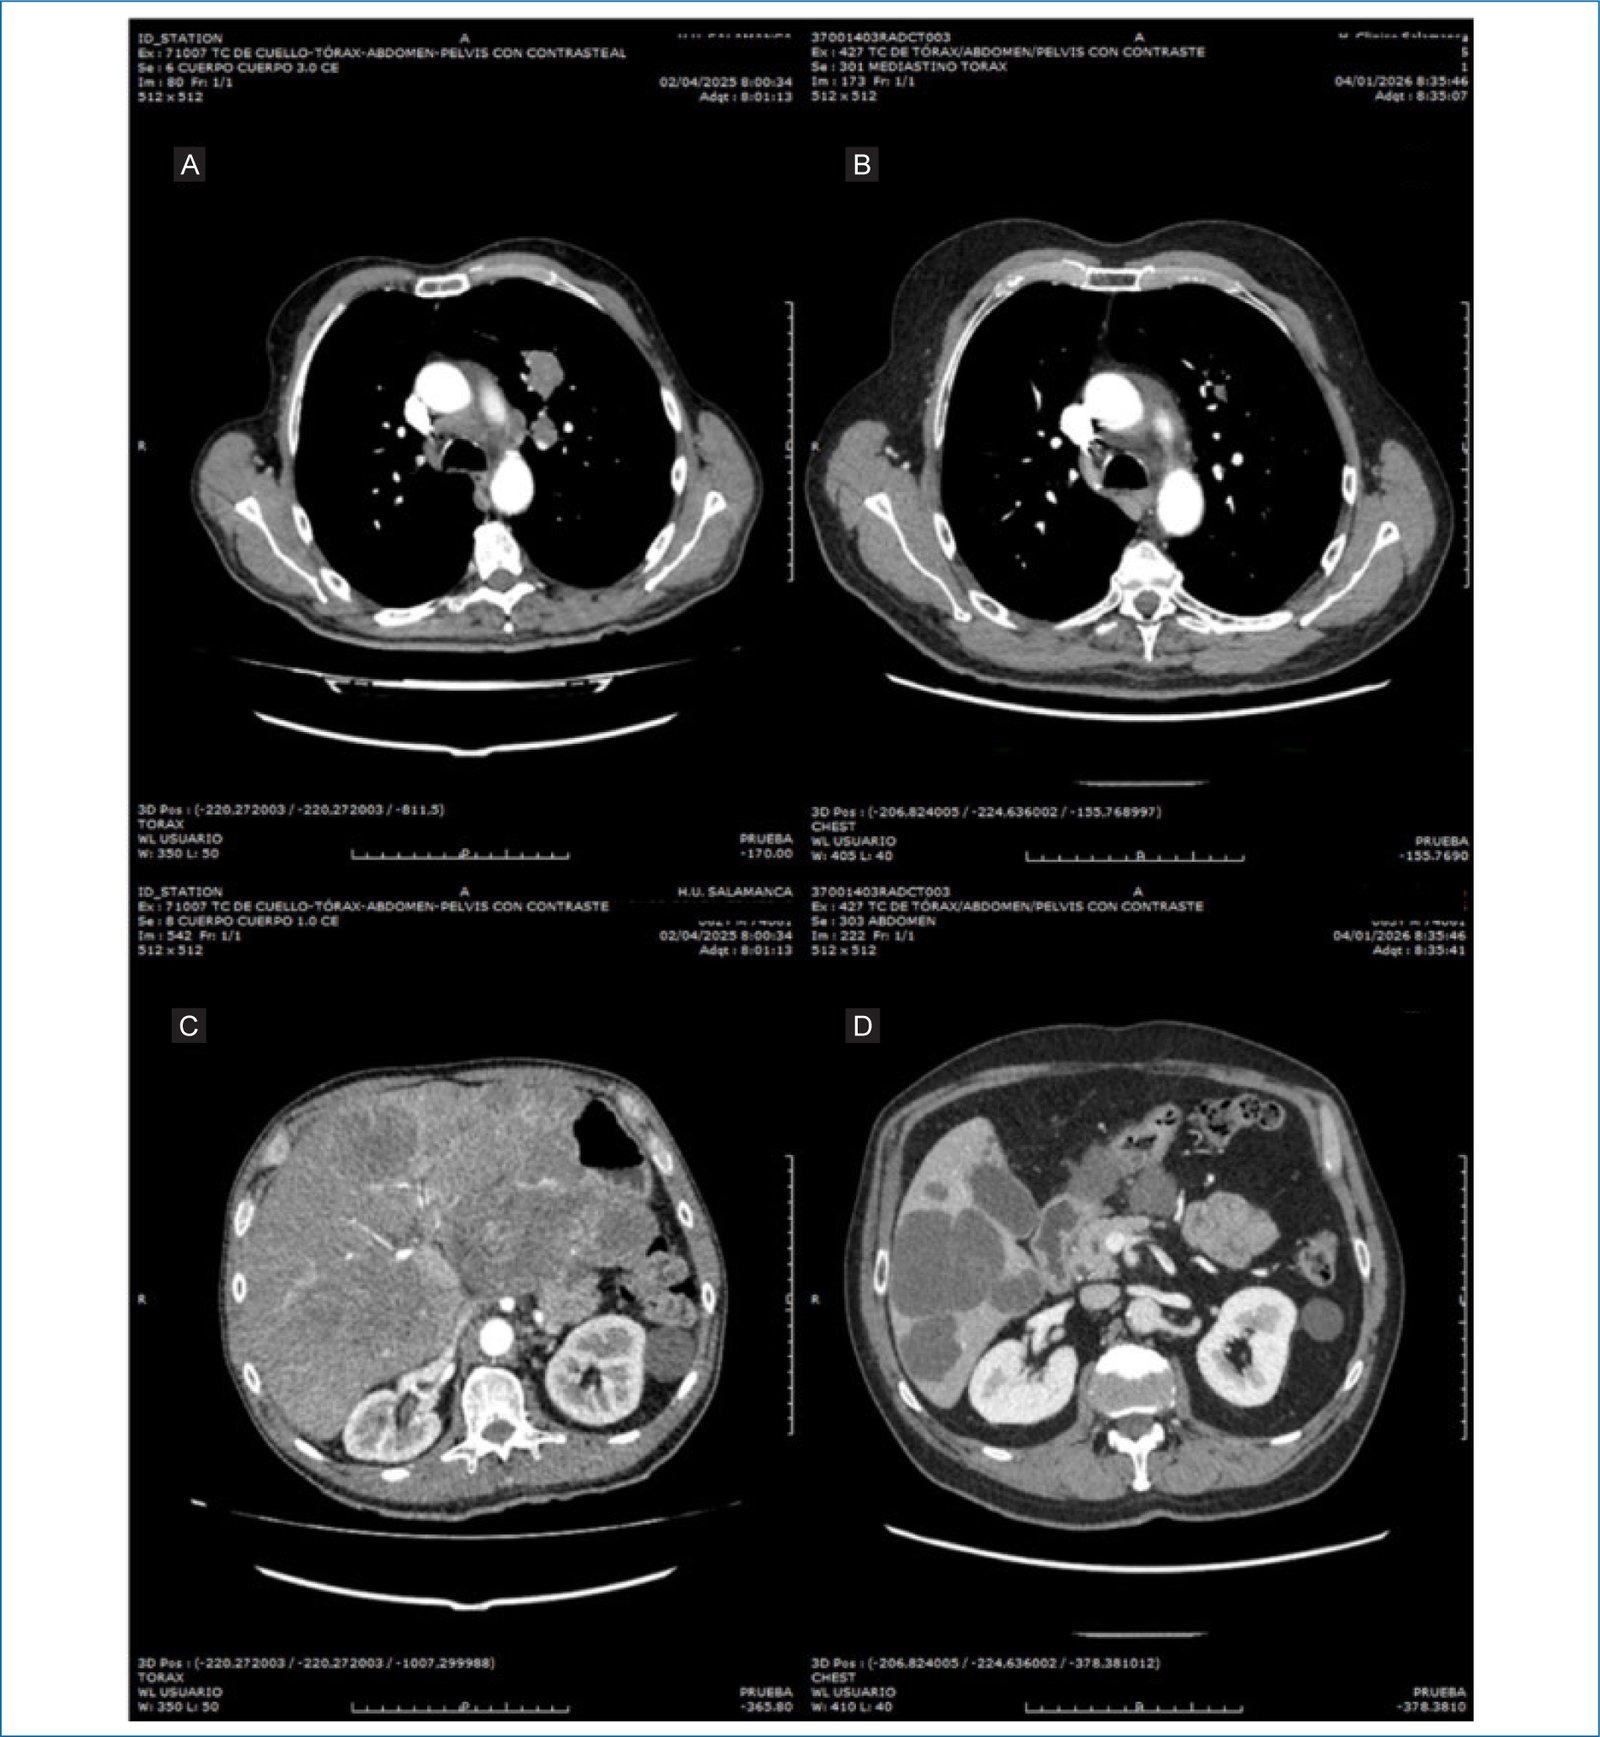
Figure 1. A and C: diagnostic computed tomography (CT) images (April 2, 2025). B and D: CT images from the most recent radiological assessment (January 4, 2026).
Chemotherapy with carboplatin-etoposide was started on April 23, 2025, due to the high aggressiveness of SCLC and the need for urgent treatment, with concurrent radiotherapy added from the third cycle. Following initiation of chemotherapy, there was marked worsening of liver function tests (Table 1). Therefore, imatinib 400 mg daily was started concurrently, with granulocyte colony-stimulating factor prophylaxis due to high risk of myelotoxicity. After informed discussion with the patient, the risks of combined toxicity were accepted given the severe clinical presentation but expected rapid response of both tumors. Chemo/radiotherapy was completed on June 25th, 2025 (45Gy in 30 fractions concurrent with four cycles of carboplatin + etoposide). The first radiological assessment in August 2025 demonstrated a partial response with significant reduction in size of the pulmonary mass and left hilar lymphadenopathy, together with marked shrinkage of both the hepatic metastases and the lesion in the gastro-hepatic ligament/lesser sac, with reduced mass effect on the stomach and pancreas.
Table 1. Liver function tests prior and after initiation of imatinib
| Liver function tests | Before imatinib | Two weeks after imatinib | Currently |
|---|---|---|---|
| ALT (U/L) | 192 | 24 | 25 |
| AST (U/L) | 181 | 13 | 13 |
| GGT (U/L) | 1543 | 346 | 72 |
| ALP (U/L) | 569 | 212 | 64 |
ALT: alanine aminotransferase; AST: aspartate aminotransferase; GGT: gamma-glutamyl transferase; ALP: alkaline phosphatase. Reference values: ALT: 10/49 U/L; AST: 35 U/L; GGT: < 73 U/L; ALP: 46-116 U/L.
Prophylactic cranial irradiation was also administered (25 Gy in 10 fractions completed on August 20th, 2025). Therefore, consolidation immunotherapy with durvalumab was initiated according to the ADRIATIC trial schedule (currently six cycles), while imatinib was continued uninterrupted.
The most recent CT scan (January 4, 2026) showed complete response of the left upper lobe mass and hilar/mediastinal lymphadenopathy, with only residual cicatricial linear lesions in the anterior segment of the left upper lobe, consistent with complete radiological response of the SCLC. In the abdomen, hepatomegaly with lobulated contours persisted, along with multiple cystic-appearing hepatic lesions (largest 6.4 cm in segment VI) and a 10 × 6.5 × 5.5 cm cystic lesion in the gastro-hepatic ligament adjacent to the lesser gastric curvature. These lesions showed size reduction and cystic transformation due to necrosis, indicative of partial response of the metastatic GIST (Fig. 1). As of January 2026, the patient remains asymptomatic with ECOG 0 and continues maintenance therapy with imatinib and durvalumab consolidation (sixth cycle administered).
Discussion
This case illustrates an exceptional presentation of two synchronous neoplasms: limited-stage SCLC with mediastinal nodal involvement and metastatic gastric GIST with extensive hepatic disease. The synchronous coexistence of SCLC and GIST is extremely rare in the medical literature.9–11 Phan et al. reported a 52-year-old female with limited-stage SCLC treated with chemoradiotherapy who achieved complete response and, 2 years later, developed a pancreatic lesion confirmed as CD117- and DOG1-positive GIST. Because the patient declined surgical resection, systemic imatinib was started, with initial nausea, vomiting, and cramps that were medically controlled. After 40 months of follow-up, she remained free of metastatic disease.9 Unlike that metachronous case, ours involves synchronous diagnosis with truly concomitant treatment of both malignancies. Girard et al. described a 49-year-old male with SCLC (8 cm mass and bilateral mediastinal nodes) plus a 1 cm nodule on the lesser gastric curvature initially considered metastatic. He received doxorubicin-etoposide-ifosfamide chemotherapy and achieved partial response. After four cycles, he developed gastrointestinal symptoms (hematemesis, anemia, dysphagia, and ascites); endoscopy revealed gastric GIST positive for CD117/c-KIT. Chemotherapy was discontinued and imatinib started at standard dose. After 3 months, CT showed marked response of the gastric lesion but pulmonary progression. Chemotherapy was reintroduced concurrently with imatinib for three additional cycles, but the SCLC continued to progress, and the patient unfortunately died 11 months after diagnosis.11 In 2020, Liu et al. reported a triple synchronous primary malignancy (pT1 SCLC, stage I jejunal GIST, and stage IIIB rectal adenocarcinoma). After multidisciplinary discussion, SCLC was prioritized due to low bleeding/obstruction risk of the gastrointestinal tumors. The patient received three fractions of stereotactic fractionated radiotherapy plus cisplatin-etoposide chemotherapy, with good response. Both gastrointestinal tumors were subsequently resected, followed by adjuvant chemotherapy (four cycles of cisplatin-etoposide plus capecitabine for the rectal cancer). No medical therapy (imatinib) was used for the GIST.10 A comprehensive search of PubMed and National Institutes of Health databases identified no reports of imatinib combined with carboplatin-etoposide and durvalumab, nor data on pharmacokinetic interactions or synergistic toxicities in similar oncologic settings. Therefore, this is the first reported experience of combining imatinib with chemotherapy, radiotherapy, and immunotherapy.
Despite theoretical risks of myelotoxicity and hepatotoxicity/pneumonitis, the patient tolerated the regimen without serious complications, maintaining ECOG 0 and remaining asymptomatic at 9 months of follow-up. The favorable evolution – with complete radiological response of the SCLC and partial response of the metastatic GIST – suggests that, in carefully selected patients with synchronous tumors and good performance status, an aggressive yet integrated multimodal approach can optimize outcomes while avoiding delays in treating the more aggressive neoplasm (SCLC).
Conclusions
Finally, with the increasing use of immunotherapy and improved survival in lung cancer patients, concomitant administration of tyrosine kinase inhibitors (such as imatinib) with immunotherapy is likely to become more frequent. At present, there is closed recruitment for the phase II clinical trial of GECP with pembrolizumab, lenvatinib, and chemotherapy combination in first-line ES-SCLC(NCT05384015). These data will help clarify these treatment combinations in terms of safety and benefit in terms of survival. Consequently, it is imperative to investigate potential drug interactions that may affect treatment efficacy and safety.
Funding
None.
Conflicts of interest
The authors declare no conflicts of interest.
Ethical considerations
Protection of human subjects and animals. The procedures followed were in accordance with the ethical standards of the responsible institutional committee on human experimentation and with the Helsinki Declaration of the World Medical Association. Procedures were approved by the Institutional Ethics Committee.
Confidentiality, informed consent, and ethical approval. The authors have followed institutional confidentiality protocols, obtained informed consent from the patient, and received approval from the Ethics Committee. SAGER guidelines were followed according to the nature of the study.
Declaration on the use of artificial intelligence. The authors declare that generative artificial intelligence was used as a tool for language revision of this manuscript.
